


Twenty years after I wrote Transdermal Magnesium Therapy, magnesium remains one of the most important—and in many settings still underappreciated—minerals in medicine. Magnesium participates in hundreds of enzymatic reactions and is fundamental to ATP metabolism, electrical stability, muscle and nerve function, glucose metabolism, vascular physiology, and normal cellular function. Magnesium is central to life, along with oxygen and carbon dioxide.
Magnesium deficiencies disrupt many biochemical functions in the human body, especially the nervous system. Thus, we can expect many magnificent, significant, and even surprising effects when we take magnesium medicine seriously, which doctors don’t do.
The cardiovascular importance of magnesium is particularly difficult to overstate. Cardiac cells depend upon tightly regulated movement of magnesium, potassium, sodium, and calcium. Magnesium participates in membrane stability and electrical conduction and influences vascular smooth muscle. Severe magnesium deficiency can therefore produce neuromuscular and cardiovascular abnormalities, including abnormal rhythms. This is one reason magnesium status deserves attention in patients with cardiovascular disease rather than being regarded as an obscure nutritional detail. The last thing you should expect or trust is your doctor’s knowledge or recommendations on magnesium.
Cancer adds another layer to magnesium’s importance. Magnesium is necessary for normal DNA synthesis and repair, energy metabolism, antioxidant defenses, immune function, and cellular signaling. These relationships make magnesium status relevant to general cellular health. Bottom line: ATP and thus oxygen utilization in the mitochondria is magnesium-dependent; low ATP pushes cells into fermentation, the hallmark of cancer metabolism.
In the news today, we read that about 71.5% of adults in the United States say they experienced fatigue on multiple days over the past three months, according to a new report from the Centers for Disease Control and Prevention’s National Center for Health Statistics (NCHS). Women and younger adults are more likely to report frequent fatigue, meaning most days or every day, than men are. Knowing that it is a biological fact that magnesium deficiencies are becoming endemic, I find it interesting and tragic that mainstream medical news and doctors hardly ever pay attention to it as a cause of disease, or of this fatigue, so it is hardly ever prescribed. Almost everyone is under increased stress these days, and stress eats up magnesium reserves like a hungry beast.

It is a vicious cycle almost no one is taught. Stress → Magnesium Loss → More Stress. Stress burns it: Adrenaline and cortisol spike to deal with stress. To make those stress hormones, to tense muscles, to fire neurons faster, your cells burn through ATP. Every ATP molecule needs magnesium to work.
Result: stress pours magnesium out in the urine. Literally, low magnesium makes you stress more: Magnesium is the brake pedal for your nervous system. It’s the gatekeeper for the NMDA receptor; it calms the HPA axis; it helps you make GABA. When you’re low, you’re wired, anxious, can’t sleep, your heart pounds, and blood pressure creeps up. Then you lose even more: Poor sleep, high cortisol, high blood pressure — all increase magnesium demand again. The hungry beast gets hungrier. Stress is a magnesium-draining machine.
If you’re chronically stressed, magnesium isn’t a luxury supplement—it’s arguably one of the few interventions that directly targets the physiology of the stress response rather than just masking symptoms with a pill.
Magnesium Chloride
Perhaps the greatest advantage of magnesium chloride is therefore not that it represents a magical form of magnesium, but that it is practical, soluble, inexpensive, and extraordinarily adaptable. It can provide magnesium orally in a readily soluble form. It can be formulated for topical application. It has inspired investigation of alternative routes of magnesium administration and, more broadly, helped shift attention toward the skin as a biologically active therapeutic interface.
Discussions of magnesium often treat all magnesium compounds as interchangeable. They are not. Physiology needs the magnesium ion, but the accompanying molecule or salt influences solubility, gastrointestinal tolerance, elemental magnesium content, formulation, and the routes through which magnesium can practically be administered.
Among the available forms, magnesium chloride is particularly versatile. It dissolves readily in water and can be used orally and in concentrated topical solutions commonly called magnesium oil, which is 35% magnesium chloride. The National Institutes of Health notes that magnesium chloride, citrate, and all forms of magnesium generally have better oral bioavailability than poorly soluble magnesium oxide. This distinction matters because the amount printed on a bottle means little if the compound does not dissolve efficiently enough to make its magnesium readily available for intestinal absorption.
Magnesium oxide illustrates the problem particularly well. It contains a large percentage of elemental magnesium by weight, which makes it look impressive on a supplement label, but it is poorly soluble. A classic human comparison found magnesium citrate considerably more soluble and bioavailable than magnesium oxide. Magnesium chloride likewise belongs to the group of soluble magnesium salts recognized as relatively well absorbed. In practical medicine, therefore, the question should never be, “How many milligrams of magnesium are in this tablet?” The more useful question is, “How much usable magnesium is actually being delivered?”
Chloride itself should not be treated as an undesirable passenger. Chloride is an essential electrolyte. It participates in extracellular fluid balance, electrical neutrality, gastric hydrochloric acid production, and acid-base physiology. The body is fundamentally an electrolyte system, and sodium, potassium, magnesium, calcium, chloride, bicarbonate, phosphate, and other ions constantly interact. Magnesium medicine should therefore be understood within this larger mineral and acid-base environment rather than as the administration of an isolated nutrient.
This brings us to the idea that made Transdermal Magnesium Therapy different when I wrote it: the skin as a potential therapeutic interface. You can apply concentrated magnesium chloride solutions directly to the skin, use them in baths and footbaths, or incorporate them into topical preparations. This creates practical possibilities that oral supplementation does not provide.

Oral magnesium is limited in some people by gastrointestinal tolerance; sufficiently large quantities of many magnesium salts can cause loose stools and diarrhea. Topical magnesium chloride does not create that particular gastrointestinal limitation. It can also be applied directly over muscles and other areas where people experience tension or discomfort.
However, the clinical literature has not established that large quantities of magnesium chloride reliably cross normal intact human skin and enter the systemic circulation. Reviews of transdermal magnesium have consequently concluded that claims of substantial systemic replacement through intact skin remain insufficiently demonstrated. This is, of course, mainstream misdirection. The skin is highly permeable. People actually can feel the effect of transdermal magnesium application.
John Abernethy (1764–1831), the English surgeon, did carry out early experiments on cutaneous gas exchange. He demonstrated that the skin could absorb gases, and his work suggested a gradient: oxygen was absorbed most readily, followed by carbon dioxide. The skin performs a small amount of gas exchange, but on a minute scale.
Transdermal drug delivery (magnesium, DMSO, nicotine patches, hormones) exploits the skin’s permeability Abernethy was probing, and topical oxygen and carbon dioxide therapies exist for wound healing. The skin is a selectively permeable, metabolically active organ through which therapeutic substances can enter the body, with penetration determined by the substance, formulation, concentration, and condition of the skin barrier.

The skin is not an impermeable wall, though some pretend it is. Thus, sun blockers can have toxic consequences; their chemicals do reach the bloodstream.
Early laboratory work suggests possible passage through hair follicles and other appendages. Thus, the scientific question should not be reduced to the simplistic claim that “nothing crosses the skin.” Still, topical application should not automatically be equated with intravenous or oral magnesium delivery. Combining approaches is the most effective option.
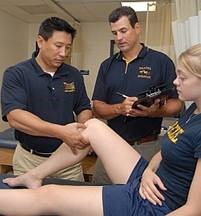
Transdermal magnesium therapy offers an exciting breakthrough in sports medicine. Coaches can now treat injuries, prevent them, and increase athletic performance all at the same time. Magnesium Oil enhances recovery from athletic activity or injuries. It reduces pain and inflammation while promoting faster tissue regeneration. Topical magnesium chloride application increases flexibility, which helps prevent injury. It also increases strength and endurance. Transdermal Magnesium Therapy benefits athletes, coaches, and sports medicine doctors.
A topical treatment does not necessarily have to produce a dramatic rise in serum magnesium to have local biological effects. Skin, superficial nerves, connective tissues, muscles, microcirculation, hair follicles, and sweat glands form a complex biological interface. Local effects and systemic mineral replacement are separate scientific questions and should be investigated separately.
Pain relief and muscle relaxation for people with arthritis and muscle cramping are significant benefits of magnesium oil. Magnesium applied directly to the skin alleviates chronic pain and muscle cramps and, in general, makes our job of opening up and softening muscles and connective tissue much easier.
When treating severe chronic disease, combining oral, intravenous, and topical approaches is the best way to address magnesium deficiencies. Oral magnesium provides a proven route to increase magnesium intake and correct inadequate dietary supply. Topical magnesium chloride provides a convenient way to expose particular tissues and skin surfaces to a concentrated magnesium solution without placing additional magnesium directly into the gastrointestinal tract. Rather than insisting that one route must replace the other, the more useful question is what each route can accomplish.

There are also circumstances in medicine where gastrointestinal absorption is insufficient or too slow. Intravenous magnesium demonstrates dramatically that route matters. Magnesium sulfate and chloride given intravenously have established medical uses, including prevention and treatment of seizures in severe preeclampsia/eclampsia and selected severe asthma exacerbations. The rapid physiological effects of intravenous magnesium remind us that magnesium is not merely a nutritional supplement. Under appropriate circumstances, it is a genuine medical intervention.
Modern medicine often measures serum magnesium and assumes the resulting number fully describes magnesium status. It does not. Only a small fraction of total body magnesium resides in serum.

Twenty years after Transdermal Magnesium Therapy, I would therefore argue more broadly rather than more narrowly. Magnesium medicine is route-dependent medicine. Oral, topical, intravenous, and potentially other delivery systems are not interchangeable.
One of the best forms of magnesium is actually magnesium bicarbonate drinking water. It is the best form of magnesium and the best form of bicarbonate, though not the strongest form, but certainly the most absorbable form.
Dr.Sircus is a reader-supported publication. To receive new posts and support my work, consider becoming a free or paid subscriber.
Subscribe now

comments